Thanks Lizze, happy with your positive reflections and great questions. Short answers below;
Usage over time
Usage typically builds up gradually after go-live and starts plateauing at around three to six months, after which it remains stable. In two Rwandan NICUs, server data showed use above 75% of hours (average hours in use per monitor per 24 hours), and some sites have used IMPALA routinely for up to four years.
The challenges we see are the common ones for health technology in these settings: staff turnover, wear and loss of accessories, and power and connectivity. Our service model was designed to address these challenges:
Staff turnover: ward champions, refresher training and e-learning, so new staff can be trained on site without waiting for us.
Equipment: sensor packages and accessory replacement are part of the service, and local distributors and biomedical partners maintain and repair on site.
Uptime: a remote dashboard flags connectivity, usage and device problems early, and software is updated remotely.
Adoption: a week of on-site training at go-live, remote follow-up after one week, four weeks and three months, then quarterly check-ins.
Despite that we still experience challenges at some sites, so it remains something that has our continuous attention.
Time savings
It's per day, not per shift. I accidentally called it per shift in earlier comments. It is self-reported by 24 staff at the Zomba Central HDU (Mwale et al. 2025), so your gut check is fair. A stronger measure: observation of 85 nursing shifts in two Rwandan NICUs showed median time per shift spent measuring vital signs falling from 28.1 to 4.2 minutes (Dzekem Dine et al. 2026). Neither captures time spent responding to alarms, which is the cost you point to. We tune alarm settings to limit it: a 15-second alarm delay cuts threshold alarms by 45%. Additionally we have introduced age specific alarm limits and made it intuitive to adjust alarm limits for individual patients.
On logging: the monitors have no user login; on the tablets staff select their name when entering data, so we can attribute entries but not measure time per user. The server logs monitor use, alarms and acknowledgements. Time in the app would also be a weak proxy, because most of the work happens at the bedside. In the future we would like to measure alarm-response time directly.
Existing bedside monitors
Mostly not. The usual baseline is manual checks with a few handheld or mobile devices; before IMPALA, the Zomba HDU had two mobile monitors, one pulse oximeter and a wall monitor that did not work. Where monitors exist, they are typically a few units in an ICU or HDU, without a ward overview or service model. Larger referral hospitals are the exception, and that is where integration matters most.
Unexpected responses
Mothers used the monitors to follow their baby, alert nurses and time breastfeeding.
Ownership spread across the whole ward team, including cleaners and caregivers.
At the Zomba HDU, admissions tripled after go-live (see case mix below).
Staffing
We don't track this systematically. "We are not aware of any site that reduced nurse staffing after implementation." Staffing is mostly set by ministries or hospital management. How freed-up nurse time is reallocated is a good question for future evaluation. We have some evidence that now more time is going to decision making. Additionally some doctors mentioned to me specifically that they now have time for lunch (seems trivial but actually is a reflection of how busy they are)
HDU case mix
Yes, it changed substantially. The post-IMPALA cohort was much sicker: multimorbidity rose from 9.7% to 42.7% and malaria from 14.5% to 45.7%, admissions tripled, and the periods covered different malaria seasons. A likely explanation is that sicker children were moved into the HDU once monitors were available, but we have not tested this. Also it could have been die to the broader increase in admissions. The case-mix-adjusted estimate (−9.8 pp, 95% CI −26.5 to 5.0) is not significant, and Rethink Priorities considers it unreliable. So the crude HDU mortality says little; critical illness events and the neonatal estimates are more informative and are an important intermediate outcomes towards mortality.
Integration
Agreed, integration is a condition for scale. IMPALA runs offline-first on a local hospital server, with data structured per patient, encounter and observation (following the FHIR resource model). A FHIR interface is not live yet. Our first EMR integration is contracted at Kenyatta National Hospital (vitals and early warning scores into the EMR); national EMRs in Malawi, Rwanda and Tanzania and DHIS2 reporting are planned. In hospitals without monitoring this has not been a barrier. In hospitals with an EMR, integration avoids double documentation, and ministries/hospitals can see it as an important benefit for procurement. Having said that, there is hardly any equipment integration into EHRs.
Tracking across admissions
Not yet. Each admission is recorded as an encounter with the hospital ID, so linkage is possible where IDs are reliable, but it is not built. Twins are registered as separate patients. Post-discharge mortality is a gap in our evidence; it needs follow-up outside the hospital. We are seeking funding to integrate Smart Discharge (University of British Columbia) for this.
Thanks again. If you're interested in also happy to jump on a call.
Thanks for the reply. In one of my other comments below I have tried to capture this by including the effect of spending funding in 3 different scenario's (0 effect, Rethink priorities and our current measured effects). In my view we should balance the chance of upside against the risk for downside (no effect) and based on that assess what will be the most likely effect size given the different scenario's including the counterfactual.
I am meeting with Nick later this week to discuss further. Happy to meet up with you as well. Also think it could be interesting to organize a dedicated discussion with a small group on this topic, because I think this is exactly the tension that we are investigating and I would love to reach consensus on how to model this well and help to better inform decisions about funding promising early-mid stage innovations.
Thanks again for the contributions to this post. The critical questions made me realise I/we had a blind spot. I took the existing evidence on monitoring so much for granted that we never built a proper overview of it, so the question of how IMPALA’s results compare to the wider literature was not well answered. Over the weekend I tried to fix that leveraging Claude to create a more structured overview.
How I approached it
The question is not whether monitoring should be done. It’s a core care process and nobody would argue for stopping it. The question is whether improving it in low-resource settings reduces deaths, and by how much. Beyond chance and study design, which we acknowledge, these are the reasons we think effects in our setting with IMPALA can be larger than in most published studies:
Very low baseline monitoring. Current practice falls far short of guidelines because of staff and equipment shortages. In Kenyan county hospitals, sick children received a median of 9 of 18 recommended observations in the first 48 hours, the period when most inpatient deaths occur. Many published studies started from good monitoring practice, so there was much less to improve.
High event density. Mortality and critical illness events are far more frequent than in high-income trials, which leaves more room for an effect and makes one easier to detect. EPOCH, the largest paediatric early-warning trial, had mortality below 0.2%. At that level even a real 20% reduction is undetectable.
It reduces workload instead of adding to it. Staff shortage is one of the biggest constraints on quality of care. Many monitoring interventions, such as paper early warning scores, add work. IMPALA automates repetitive tasks; nurses in the Zomba HDU reported monitoring time falling from 3.3 to 1.8 hours per shift. That figure is self-reported, and the effect on other care tasks has not been measured directly.
The response is simple, but it’s the weak link. Managing critically ill children and newborns is mostly about restoring balance: oxygen, fluids, antibiotics, temperature management, and stimulating a newborn with apnoea. These treatments are simple and mostly present, but the evidence shows they often don’t reach the right patient at the right time. That’s why we pair the technology with emergency-care training and ward champions.
It’s a care package, not just a device. IMPALA combines equipment, software, training and ongoing service support, aimed at lasting behaviour change. In many ways it is more similar to packages like Helping Babies Breathe, the Safer Births Bundle of Care and E-MOTIVE which have also demonstrated large effect sizes.
What the evidence shows
Monitoring alone, randomised: effects range from none (EPOCH, CRADLE-3, CRADLE-5) to 22% lower mortality (HeRO, very-low-birthweight infants in the US). The clearest lesson is that better detection alone doesn’t save lives; detection has to trigger a response that is actually delivered.
Early warning and response systems in children: pooled and quasi-experimental studies converge on roughly 15–20% lower mortality.
Care bundles in East Africa: 18–47% fewer early deaths, with randomised support from Safer Births (24-hour neonatal deaths aRR 0.61) and E-MOTIVE (severe bleeding outcomes RR 0.40).
IMPALA: our paediatric ward estimates (about 40–50%) are above every randomised estimate for monitoring alone and closer to those for bundles. They come from one retrospective before–after study, which the review rates as very low certainty. Our neonatal results range from no change to 35% lower mortality across five units, with 2 of 5 statistically significant.
What this means for the RP estimate: at a ward mortality of about 4%, a 15–20% reduction would be 6–8 deaths averted per 1,000 admissions. RP’s discounted 12% sits below that range. The external evidence supports a benefit of that order; it doesn’t establish effects of 40% or more.
What would settle it: the central gap is that no randomised or concurrently controlled trial of continuous ward monitoring exists in any low-resource setting. That is the strongest argument for the trial we have been trying to fund.
Below this post are the most important figures that summarize all findings from all studies we identified to create an intuitive visual overview of current evidence including how our findings relate to them.
Caveats
This is a structured narrative review, not a systematic review. It was written by one reviewer with AI assistance, in a short time, and it’s the best we could do in that time. Every figure links to its source. The document includes the prompt we used, so anyone can rerun the review with another AI model and compare results. We’ll revise it as we go and would welcome comments, questions, corrections and missing studies, either here or directly in the document.
Separately, I’m still waiting for responses from the study authors and from Rethink Priorities on Martijn’s points, and will share them here when I have them.
Niek
@Martijn Klop 🔸 @Britta Jewell and @NickLaing tagging you as I would really value your reflection of this evidence, the approach to build it like this and if you may have questions, inputs and suggestions for improvement.
Thanks for acknowledging the difference between us and monitoring. It is very important to me that people see it is not just about putting a monitor down.
As with regards to confounding factors,
Everything was modelled for seasonality. (that is why we always compare a full year)
As with regards to sickness of patients --> this was corrected for by comparing individual patient characteristics and matching them on propensity score in the pediatric study.
Patient numbers were looked at and there were both significant increases and decreases. Hard to say what the impact of that was on mortality.
In all sites we have done qualitative interviews to assess if there were any other programs or changes that could explain the difference. We did not identify them. Health workers themselves attributed it to IMPALA.
As with regards to should the zero still be included. Maybe at this point yes, but as we progress and we get results from more hospitals with similar results a zero results becomes increasingly.
What I would like to put in here: let us assume Rethink priorities assessment as the base case with our current results as the upside scenario, the zero case would be the worst case (think we can agree that a negative effect of monitoring would be highly unlikely?)
My point is that we should not wait until we have certainty that it is not zero, but that we should act on what is the most likely case at this stage, because that is what will determine the return of investment. In this we should not just look at what the procurement buys now, but also on what effect it will have downstream.
We often call this the impact business case: the impact per hospital, how many hospitals we can reach in a given time (through sales, donations and programs), and the total impact per year that follows. Set the growth numbers and you get a low, medium and high estimate of impact over time. Every piece of evidence reduces the uncertainty and improves the estimate. From this you can estimate the return on investment, balancing the risk of no impact against the potential for impact. Waiting is not free: it slows growth and growth potential, with knock-on effects downstream.
Let's say you are a fund manager (or several funders making the same call) with three options:
A) A USD 500k grant, in line with our base case: about 1,170 new hospitals by 2030.
B) No funding: wait for a trial or more results. We assume about 15% fewer hospitals by 2030 (about 990). At our current stage USD 500k has an outsized effect: without it, the risk of operational disruption and bankruptcy rises, and other funding would likely shrink too, because EA funding decisions are closely linked.
C) Double down with USD 2.5M for scale-up and further evaluation: about 15% more hospitals than the base case (about 1,340).
And three impact scenarios, roughly normally distributed:
Median: Rethink Priorities' estimate, 12% fewer deaths on pediatric wards and 7% in neonatal units
Low: 5% chance: zero or negative effect
High: 5% chance: our measured effects (42% for children, 26% for neonates, as weighted in RP's report) are true, or higher
The outcome, in DALYs averted by the end of 2030:
Under these assumptions, the USD 2M catalytic grant (C instead of A) has about a 93% chance of beating the same money given to Helen Keller Intl's vitamin A supplementation, a GiveWell top charity. It breaks even at about a 1% cut in in-hospital deaths. Median return: about 359,000 DALYs, 9.8x vitamin A. Expected return: about 500,000 DALYs, 14x. If the measured effects hold: about 1.3 million. - The cost of waiting (B): at the median, about 175 fewer hospitals and 359,000 fewer DALYs than A, and 718,000 fewer than C. In expectation, about 500,000 and 1.0 million fewer.
With growth moving 15% either way, waiting costs about as much as the grant adds. If IMPALA has no effect, no option averts anything, and the USD 2M would have done more at vitamin A: about 36,600 DALYs, or 570 lives. Research that shows this early stops spending on something that does not work.
Simply put: if you can choose between Vitamin A and IMPALA, based on this model the chance is 7% that you will get a better (social) return on investment and a 93% chance that you get a better return on investment with an upside that is a lot higher.
The model is purely for discussion. I do not want to claim any of these effects as definitive outcomes. - Question 1) do you agree with the framing of this choice and the impact business case it represents - Question 2) what are the assumptions that we use for impact and growth
Full analysis, with the model, slides and all assumptions (generated by Claude reviewed by me): https://docs.google.com/document/d/1Up2M0HCa3vhK2ouK9BmbGpXGz2EHKtKqynSyuupwJOo/edit
Thanks for this valuable comment. The RP report was the first time for me to learn about the attribution of a certain value to a life saved based on age. Once you are aware about it, you see it and understand it, but it is not really discussed. I found it quite difficult to work with these values as it somehow dilutes/obscures what the findings were. Additionally I find it morally challenging as the people who benefit from the intervention might value these lives completely differently.
Not sure how we can handle that well in our communication without getting people lost in technicalities, so if you would have suggestions for that I would greatly appreciate that.
One more addition --> we have planned to use all feedback and insights from this Forum to further sharpen our own evidence overview which we have created on notion. So our own interpretation and representation of the evidence will be improved. If you are interested, please have a look. All feedback (positive and negative) is welcome and will be used to further improve the overviews. https://goal3knowledgehub.notion.site/public-knowledge-hub?pvs=143
Specific recommendations or suggestions for further research (beyond a trial as we already have planned that but will need funding first) are also much welcomed.
Thanks Martijn. This is the kind of critical reflection we hoped for when we opened this up, and I’m grateful you took the time to go through the paper, its supplement and the review history in this much detail. These are important points, and they add nuance to how the evidence should be read.
On the conflict of interest: you are right. Our commercial interest should have been declared from the first submission, and it wasn’t until the final version. That was an oversight because we did not handle the submission process and we assumed it was done, not a deliberate choice, but it remains a mistake and I share responsibility for it as a co-author. Readers should weigh the paper with that in mind. The same applies to the RP report: GOAL 3 commissioned and paid for it.
I do want to respond to one word: “integrity.” I understand why the late COI declaration raises that question, and that one is on us. But I’d ask you to separate it from the rest of the work. The study was designed, run and analysed by researchers from six independent academic institutions in Malawi and the Netherlands, with GOAL 3 staff contributing to data collection and writing, not the analysis. The full results were published, including the HDU result that was not significant and the increase in crude HDU mortality, and the data are available for replication. Questioning the methods is fair and useful, and I will aim to get the answers as soon as possible. Questioning the integrity of the researchers, many of whom have no stake in IMPALA, is a different claim, and I don’t think that does justice to all the people who have contributed. I’d appreciate it if you’d reconsider that framing.
On the statistical points: I’m a clinician, not an epidemiologist, unfortunately the methods in this study (TMLE, the matched sensitivity analysis, how the estimates are defined) are beyond what I can judge with confidence. I don’t want to explain/defend something I can’t fully assess. I’ll ask the lead authors to respond to your points on the HDU estimate, the matched analysis, the case-mix adjustment and the data breakdown at St Luke’s, and I’ll share their answer here. The paper says anonymised data are available for replication, and I’d support an independent reanalysis. I’ll also ask Rethink Priorities to respond to your point on how they weighed this study, since that question is fairly theirs to answer.
Some broader context. I agree the Zomba HDU result can’t carry weight on its own, and that the ward-level results depend on spillover, which this study did not test directly. That’s why it may help to look at the rest of the evidence:
Neonatal units: we have five estimates from units where the monitors were actually installed, so these don’t rely on spillover. The strongest design is a controlled interrupted time series in two Malawian NICUs (Chihana et al., 2026). It found a 35% reduction at Mchinji (significant) and 27% at St Luke’s (not significant). Sengerema in Tanzania saw a 27% reduction (uncontrolled), Nyamata in Rwanda 20% (not significant), and Rwamagana no change.
Critical illness events: these fell sharply at both Malawian sites (Zomba HDU −47 pp, St Luke’s −25 pp). The study was powered for this outcome. It isn’t mortality, but it is the more precise signal and pathophysiologically very much aligned as an intermediate outcome towards mortality.
Mechanism behind spillover: health workers report monitoring time dropping from 3.3 to 1.8 hours per day. Whereas in other (unpublished) surveys in 4 health facilities with 116 participants, we have also found 92% of health workers reported reduced workloads. That makes a ward-wide effect plausible. Important to note here is that in all hospitals where these studies took place the same nurses working in the HDU are the ones taking care of the patients in the general ward.
We understand our evidence is not super-strong, eight of nine mortality estimates point in the same direction, but only some are statistically significant. None are randomised, and most were co-authored by GOAL 3 staff. A consistent direction makes chance less likely, but it doesn’t remove biases the studies share, such as before-after confounding. So my honest summary is that the evidence points towards a benefit but does not establish its size, and your critique makes clear the uncertainty is wider than a single discounted figure suggests. That’s also why we still want an independent, prospective controlled evaluation alongside scale-up, as discussed with Nick above.
Thanks again. This is exactly the kind of scrutiny that makes the evidence base better and helps to improve our understanding as well where we have blind spots and need to make additional steps, which was also one of the key reasons to ask RP to assess our evidence.
I hope the process will also help to build your confidence in us and that we are as truthful and transparent as we can be in search of improvement and sharpening our reasoning, evidence (including interpretation) and expanding our impact.
Ministries of health are not passive recipients of aid in our model, their buy-in and willingness to commit resources is fundamental for success and in our perspective the pathway to both scale and sustainability. It is indeed true however, that if I would come with funding they would gladly accept it. Increasingly we see that they are requesting funders to support in purchasing IMPALA One of the key reasons we would like to the Trial is that it will make it easier for them (and funders like UNICEF, UNITAID etc) to justify this in policy and budgeting. So at this stage we see significant buy-in and commitment from governments in the scale-up, but freeing up own resources at sufficient degree to buy entire systems is not yet feasible. We think we can also get there without the trial, but the trial would help a lot. We are also confident that we can easily deliver this trial together with our partners, as we already drafted the protocols and plans to that.
As with regards to your standpoint on RP's assessment --> would you be able to explain why you are so steadfast about it not being correct? Right now you make a claim that they are overstating the effect, but there is a 72% discount already in their estimated effect, which has been largely subjective based on study design. I wonder what arguments you would have to say their assessment is not correct and that the effect should be closer to 0 beyond the weaker study designs.
In my view the fact that the patients before and after where matched for severity in the pediatric design and that we have a controlled interrupted time series for neonatal care is also a quite strong design. (https://researchonline.lshtm.ac.uk/id/eprint/4648480/) And last but not least that all evidence points in the same direction makes chance alone very unlikely.
One thing that is also worth considering You mention the confidence interval is very large which is because the occurrence of the event (death) is quite rare. However if you look at the primary outcome of Critical Illness Events which is an intermediary outcome to mortality and is a lot more frequent, the confidence interval is a lot smaller so the claims about those are quite robust. Moreover the supportive evidence relating to impact on workload, stress levels and confidence of health workers is also important. In general our intervention achieves its effects not just through better monitoring, but also by freeing up time of health workers. This has also been quantified in multiple studies.
As with regards to other studies, I am afraid I must agree that there is hardly any good studies out there within our population. There are several studies on early warning scores, but few on monitoring and especially not in children. Why I believe it works well in this population and why this is different from many other monitoring interventions
a) it is as much about unburdening health workers and freeing up their time as it is about getting better data on what is happening with the child. Our data show health workers consistently report reduced workload and stress levels after implementation. Also direct observation shows it saves a lot of time (from 3.3 hours per shift to 1.8 hours per shift)
b) these are very high risk children, the standard of care is very little if any monitoring, it is easy to improve from there and get better outcomes
c) interventions are relatively simple and readily available (IV fluids, oxygen, antibiotics and glucose, for neonates it can be as simple as rocking the body to prevent severe apnea)
d) as mentioned it is not just monitoring, it is embedded in an entire program of training and continued support with a quality improvement component. Therefore we address a much broader range of potential barriers to timely, quality care then just the lack of vital signs monitoring
In general I feel that there is a huge lack of attention on monitoring in these settings. It is often an afterthought and even in very large programs oxygen and other treatments are prioritized over other things. So for me this is one of the main reasons our effect sizes can be so great. To me monitoring is the foundation of hospitalized patients, especially the most critical/vulnerable patients. The lack of attention on this and lack of awareness about the gaps are huget bottlenecks to improving quality of care.
A) We want it to be representative so only selecting referral hospitals does not do the job as it will not inform a ministry of health what will happen in rural areas. The challenge is that hospitals vary quite a bit, so you have to match them first for certain characteristics and then randomly assign them. The larger the variation the more hospitals you will need, hence we came at 72 through our power calculations. The challenge is most funds only go up to 2 or 3 million USD
B) I think you are right from where we are today, but there have been many moments where it was likely we would not survive. We have our own development team, registrations to maintain all requiring significant investments. If it takes too long, likelihood of dying in the valley of death will increase. There are very few innovators who are actually successful in public health systems for this reason.
Scaling slow also has high opportunity costs. We have made calculations based on our growth projections (hospitals reached) and our impact per hospital (mortality data). I can not share these now, but let's use a fictive scenario that is close to our estimates:
Let's assume Rethink Priorities assessment is right and each hospital using IMPALA will save 7 newborn lives per year and 12,2 pediatric lives per year. If we grow according to our plans we will reach~1000 hospitals by 2030 and IMPALA will help avert ~19,200 deaths every year.
If this is delayed and only 500 hospitals are reached, this means a difference of ~9,600 lives saved in a single year and cumulatively a lot more. At the levels of our own results this would be 4-5 times higher. Of course I also understand it could be significantly lower (but as rethink priorities said even at 1-2% reduction it would still be a good investment). The longer we wait the higher the opportunity costs will be.
My point is not that we should release all breaks and all funding should go to us to scale. However I think it is more than justifiable to invest significantly in a large(r) scale program with thorough evaluation, which could yield results a lot faster and generate more decision critical evidence.
As a few follow-up question to you (and the rest of the forum): What study results (number of sites, quality etc), not from a trial, would convince you and why? If only a trial can convince you why is that? What evidence does it deliver that routine evaluation at scale could not?
C) In any research setting there will be research staff and a lot more data collection, this by itself has a huge effect on how care is provided. Moreover not all sites will be suitable for it, creating a significant selection bias. Therefore the performance in (optimal) trial circumstances often has limited meaning for what it means in real life. Moreover variations across countries, will likely influence success of the intervention. So generalizability is also limited (Why would someone in West Africa, South-East asia or the middle east believe the trial from East Africa) Real world evidence solves a large part of this, whether if it is implementation research or derived from the real world evaluation. We look at each installation for usage, adoption and impact on health workers stress and burnout, where possible (if funding allows) we look at impact on mortality. While the quality of the evidence may be lower, it says a whole lot more about what is actually happening within the specific hospital/country and provides opportunities to intervene (either through us, or the hospital itself) Seeing this over multiple hospitals in one country will help a lot more with decision making then a (potentially outdated) trial from 5000km away (as a figure of speech).
Again, not opposing a trial here just wonder if it is the right instrument for the stage we are at. Just to provide a different perspective. A 5 million implementation program, would allow me to go to 200-300 hospitals in different countries and perform a thorough monitoring and evaluation program in parallel which can look at before-after differences, but also at differences between other hospitals. Those results would be available within 1 year after implementation, so likely 2 years after a grant was awarded.
D) Don't think Claude is accurate. Without a verifiable source on the mortality drop that answer is pretty useless, beyond that it is not wise to assume a conclusion that this is common based on one site. Data quality is notoriously bad in this setting and there is severe under reporting. We have solved this by diving into individual patient files hand by hand (not us, but our research partners)
The study you cite is hardly comparable in my view - general wards versus ICU/HDU - High resource settings only - high levels of staffing and no lack of monitoring equipment - Only adults - Vast majority is surgical patients - total number of patients only 1284 over all studies combined - relative rare occurance of the events making them statistically underpowered to proove significant impact
Moreover if you dive into their discussion you also find that over multiple systematic reviews all findings are consistently positive favoring monitoring, yet not significant. That is relevant to our discussion, because one of the key conclusions is that even at 1-2% mortality reduction IMPALA would still be cost-effective against any bar.
Hi Nick, thanks for your message. Happy to jump on a call myself as well to dive deeper feel free to email ([email protected]) or text via the chat function of the forum (if it has that)
as a first quick reflection/response, hopefully I have more time later this week but here are a few reflections, and apologies for not following your exact numbering.
A) we have been trying over the past 4 years to get trials funded (EDCTP, givewell, EU funding, Gates) without success. There are some ways to make it lower cost (lowest we got was about 2,5M, but that also reduces quality and strength of evidence). In between time we have done what we could through different smaller sources of funding to get the best evidence possible. Agree by the way that blinding is not needed and not relevant and that a large effect actually comes from the behavior change due to its clear presence on the ward. Also randomization is not an issue as long as control sites also get the intervention.
B) trials can be great, but if we wait for those results to come out before scaling we would likely not survive as an organization. This is not unique for us, but for all innovations and a major bottleneck for innovative solutions in general. Moreover, 3 years of waiting to scale and finding out that the results are same, would create a huge amount of deaths not averted, happy to provide more precise estimates at a later stage. Or plea is not to skip the trial, our plea is to do it in parallel.
C) While I like trials I actually think real world evidence is better or at least as important. With monitoring and many other interventions it is not about if they work, but how do they work in a very complex environment that is under-resourced and understaffed. In other words, if I would be the minister of health, I would value evidence from 100% of 50 sites in a real world setting a lot higher than the evidence from the intervention under trial circumstances. Just to be clear --> we are doing all this (we are currently running a controlled interrupted time series in multiple countries and multiple other impact evaluations are still ongoing) and still want to do the trial if we can get the funding for it.
D) A trial as the definitive answer to answer the question if something should be scaled is not rational from a perspective of levels of uncertainty. In my view the lower bound of the margin of certainty just needs to be above (or close to) the treshhold because if it is above that level it would not be rational to say we need a trial first before scaling it up, because the statistics already say it is highly unlikely that it is. I sometimes use the picture at the bottom to describe that (NB if evidence changes the direction of the arrow may also change). Of course it is good to discuss if you agree to the estimated impact and the margins of uncertainty to that which Rethink priorities found, because I do think that is important to agree on (or disagree and find ways to close the gap)
E) too salesy --> I think you may underestimate how important the technology, service-model and business model are compared to anything else that is out there. There are dozens if not hundreds of changes we have done and are continuously doing to improve the intervention (at GOAL 3 level) and at the facility (to improve adoption and usage at facility level) all embedded in the business model which allows us to do continue to do this over time. We do not describe this here in this post to sell or brand our solution, but also to make clear that just putting a monitor down will not have the same effect.
Last but not least: it is also a product of passion and enthusiasm that comes from building 8+ years towards this solution. I just can't be fully objective in how I describe our solution. Firstly because it is the answer to the problems I experienced myself when working in the field, secondly I think there are a lot of lessons to learn from our success that can be used by others. I hope you can accept that (and maybe even appreciate it ;-) )
F) thanks again. Really appreciate the open discussion. Would be great to connect
Thanks Lizze, happy with your positive reflections and great questions. Short answers below;
Usage over time
Usage typically builds up gradually after go-live and starts plateauing at around three to six months, after which it remains stable. In two Rwandan NICUs, server data showed use above 75% of hours (average hours in use per monitor per 24 hours), and some sites have used IMPALA routinely for up to four years.
The challenges we see are the common ones for health technology in these settings: staff turnover, wear and loss of accessories, and power and connectivity. Our service model was designed to address these challenges:
Staff turnover: ward champions, refresher training and e-learning, so new staff can be trained on site without waiting for us.
Equipment: sensor packages and accessory replacement are part of the service, and local distributors and biomedical partners maintain and repair on site.
Uptime: a remote dashboard flags connectivity, usage and device problems early, and software is updated remotely.
Adoption: a week of on-site training at go-live, remote follow-up after one week, four weeks and three months, then quarterly check-ins.
Despite that we still experience challenges at some sites, so it remains something that has our continuous attention.
Time savings
It's per day, not per shift. I accidentally called it per shift in earlier comments. It is self-reported by 24 staff at the Zomba Central HDU (Mwale et al. 2025), so your gut check is fair. A stronger measure: observation of 85 nursing shifts in two Rwandan NICUs showed median time per shift spent measuring vital signs falling from 28.1 to 4.2 minutes (Dzekem Dine et al. 2026). Neither captures time spent responding to alarms, which is the cost you point to. We tune alarm settings to limit it: a 15-second alarm delay cuts threshold alarms by 45%. Additionally we have introduced age specific alarm limits and made it intuitive to adjust alarm limits for individual patients.
On logging: the monitors have no user login; on the tablets staff select their name when entering data, so we can attribute entries but not measure time per user. The server logs monitor use, alarms and acknowledgements. Time in the app would also be a weak proxy, because most of the work happens at the bedside. In the future we would like to measure alarm-response time directly.
Existing bedside monitors
Mostly not. The usual baseline is manual checks with a few handheld or mobile devices; before IMPALA, the Zomba HDU had two mobile monitors, one pulse oximeter and a wall monitor that did not work. Where monitors exist, they are typically a few units in an ICU or HDU, without a ward overview or service model. Larger referral hospitals are the exception, and that is where integration matters most.
Unexpected responses
Mothers used the monitors to follow their baby, alert nurses and time breastfeeding.
Ownership spread across the whole ward team, including cleaners and caregivers.
At the Zomba HDU, admissions tripled after go-live (see case mix below).
Staffing
We don't track this systematically. "We are not aware of any site that reduced nurse staffing after implementation." Staffing is mostly set by ministries or hospital management. How freed-up nurse time is reallocated is a good question for future evaluation. We have some evidence that now more time is going to decision making. Additionally some doctors mentioned to me specifically that they now have time for lunch (seems trivial but actually is a reflection of how busy they are)
HDU case mix
Yes, it changed substantially. The post-IMPALA cohort was much sicker: multimorbidity rose from 9.7% to 42.7% and malaria from 14.5% to 45.7%, admissions tripled, and the periods covered different malaria seasons. A likely explanation is that sicker children were moved into the HDU once monitors were available, but we have not tested this. Also it could have been die to the broader increase in admissions. The case-mix-adjusted estimate (−9.8 pp, 95% CI −26.5 to 5.0) is not significant, and Rethink Priorities considers it unreliable. So the crude HDU mortality says little; critical illness events and the neonatal estimates are more informative and are an important intermediate outcomes towards mortality.
Integration
Agreed, integration is a condition for scale. IMPALA runs offline-first on a local hospital server, with data structured per patient, encounter and observation (following the FHIR resource model). A FHIR interface is not live yet. Our first EMR integration is contracted at Kenyatta National Hospital (vitals and early warning scores into the EMR); national EMRs in Malawi, Rwanda and Tanzania and DHIS2 reporting are planned. In hospitals without monitoring this has not been a barrier. In hospitals with an EMR, integration avoids double documentation, and ministries/hospitals can see it as an important benefit for procurement. Having said that, there is hardly any equipment integration into EHRs.
Tracking across admissions
Not yet. Each admission is recorded as an encounter with the hospital ID, so linkage is possible where IDs are reliable, but it is not built. Twins are registered as separate patients. Post-discharge mortality is a gap in our evidence; it needs follow-up outside the hospital. We are seeking funding to integrate Smart Discharge (University of British Columbia) for this.
Thanks again. If you're interested in also happy to jump on a call.
Regards,
Niek
Hi Ian,
Thanks for the reply. In one of my other comments below I have tried to capture this by including the effect of spending funding in 3 different scenario's (0 effect, Rethink priorities and our current measured effects). In my view we should balance the chance of upside against the risk for downside (no effect) and based on that assess what will be the most likely effect size given the different scenario's including the counterfactual.
I am meeting with Nick later this week to discuss further. Happy to meet up with you as well. Also think it could be interesting to organize a dedicated discussion with a small group on this topic, because I think this is exactly the tension that we are investigating and I would love to reach consensus on how to model this well and help to better inform decisions about funding promising early-mid stage innovations.
Hi everyone,
Thanks again for the contributions to this post. The critical questions made me realise I/we had a blind spot. I took the existing evidence on monitoring so much for granted that we never built a proper overview of it, so the question of how IMPALA’s results compare to the wider literature was not well answered. Over the weekend I tried to fix that leveraging Claude to create a more structured overview.
How I approached it
The question is not whether monitoring should be done. It’s a core care process and nobody would argue for stopping it. The question is whether improving it in low-resource settings reduces deaths, and by how much. Beyond chance and study design, which we acknowledge, these are the reasons we think effects in our setting with IMPALA can be larger than in most published studies:
What the evidence shows
Below this post are the most important figures that summarize all findings from all studies we identified to create an intuitive visual overview of current evidence including how our findings relate to them.
Caveats
This is a structured narrative review, not a systematic review. It was written by one reviewer with AI assistance, in a short time, and it’s the best we could do in that time. Every figure links to its source. The document includes the prompt we used, so anyone can rerun the review with another AI model and compare results. We’ll revise it as we go and would welcome comments, questions, corrections and missing studies, either here or directly in the document.
Separately, I’m still waiting for responses from the study authors and from Rethink Priorities on Martijn’s points, and will share them here when I have them.
Niek
@Martijn Klop 🔸 @Britta Jewell and @NickLaing tagging you as I would really value your reflection of this evidence, the approach to build it like this and if you may have questions, inputs and suggestions for improvement.
Thanks for acknowledging the difference between us and monitoring. It is very important to me that people see it is not just about putting a monitor down.
As with regards to confounding factors,
As with regards to should the zero still be included. Maybe at this point yes, but as we progress and we get results from more hospitals with similar results a zero results becomes increasingly.
What I would like to put in here: let us assume Rethink priorities assessment as the base case with our current results as the upside scenario, the zero case would be the worst case (think we can agree that a negative effect of monitoring would be highly unlikely?)
My point is that we should not wait until we have certainty that it is not zero, but that we should act on what is the most likely case at this stage, because that is what will determine the return of investment. In this we should not just look at what the procurement buys now, but also on what effect it will have downstream.
We often call this the impact business case: the impact per hospital, how many hospitals we can reach in a given time (through sales, donations and programs), and the total impact per year that follows. Set the growth numbers and you get a low, medium and high estimate of impact over time. Every piece of evidence reduces the uncertainty and improves the estimate. From this you can estimate the return on investment, balancing the risk of no impact against the potential for impact. Waiting is not free: it slows growth and growth potential, with knock-on effects downstream.
Let's say you are a fund manager (or several funders making the same call) with three options:
And three impact scenarios, roughly normally distributed:
The outcome, in DALYs averted by the end of 2030:
Under these assumptions, the USD 2M catalytic grant (C instead of A) has about a 93% chance of beating the same money given to Helen Keller Intl's vitamin A supplementation, a GiveWell top charity. It breaks even at about a 1% cut in in-hospital deaths. Median return: about 359,000 DALYs, 9.8x vitamin A. Expected return: about 500,000 DALYs, 14x. If the measured effects hold: about 1.3 million. - The cost of waiting (B): at the median, about 175 fewer hospitals and 359,000 fewer DALYs than A, and 718,000 fewer than C. In expectation, about 500,000 and 1.0 million fewer.
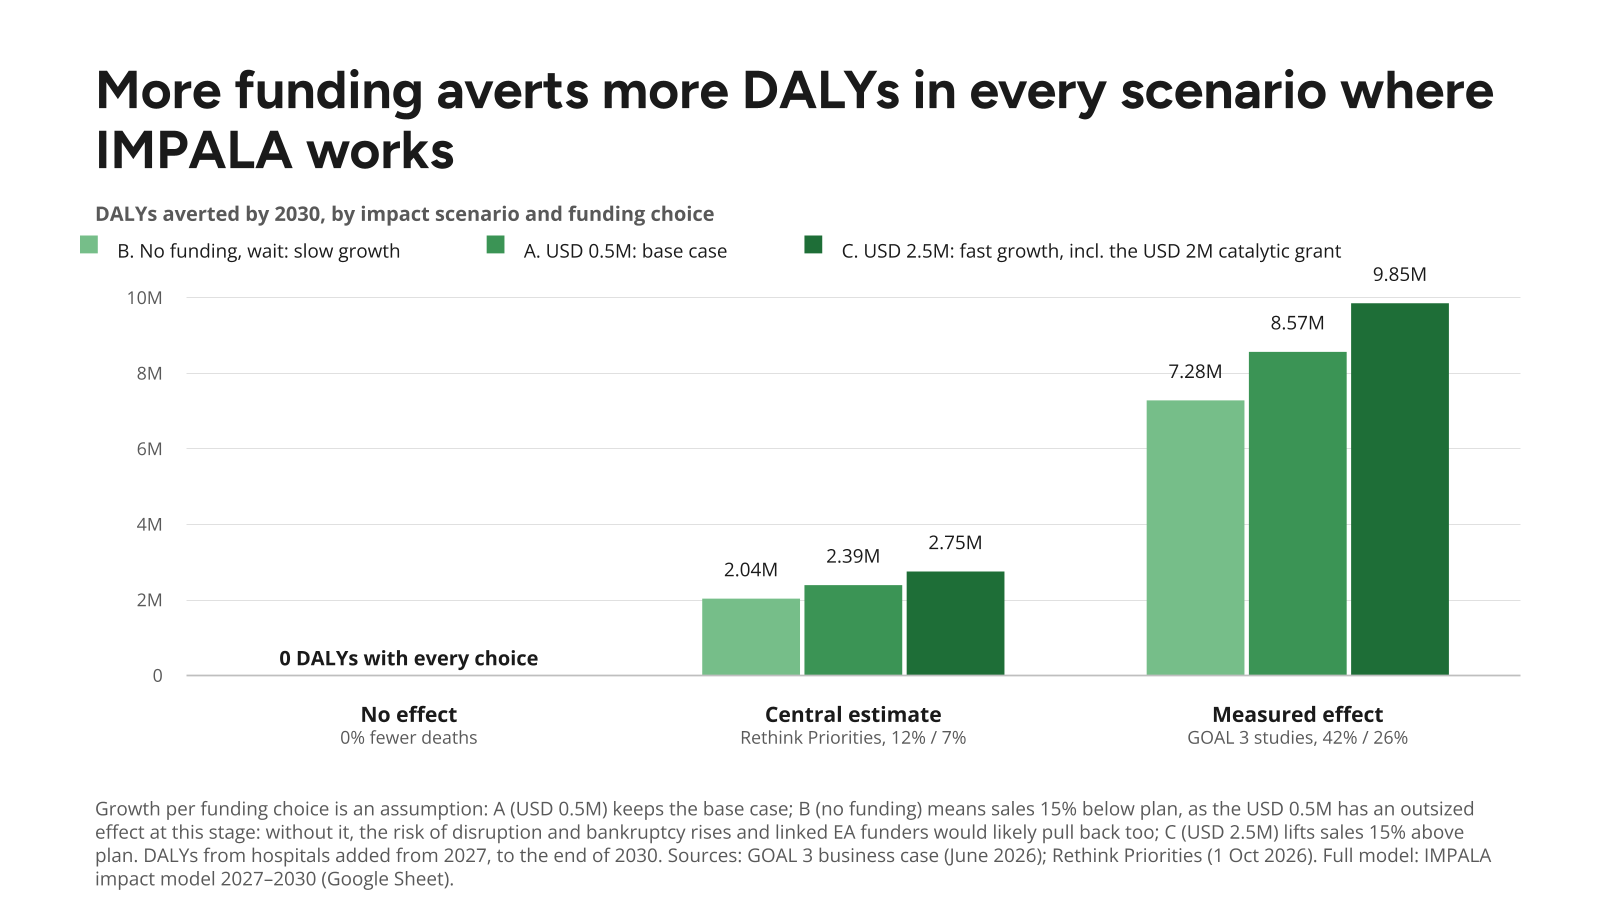
With growth moving 15% either way, waiting costs about as much as the grant adds. If IMPALA has no effect, no option averts anything, and the USD 2M would have done more at vitamin A: about 36,600 DALYs, or 570 lives. Research that shows this early stops spending on something that does not work.
Simply put: if you can choose between Vitamin A and IMPALA, based on this model the chance is 7% that you will get a better (social) return on investment and a 93% chance that you get a better return on investment with an upside that is a lot higher.
The model is purely for discussion. I do not want to claim any of these effects as definitive outcomes.
- Question 1) do you agree with the framing of this choice and the impact business case it represents
- Question 2) what are the assumptions that we use for impact and growth
Full analysis, with the model, slides and all assumptions (generated by Claude reviewed by me): https://docs.google.com/document/d/1Up2M0HCa3vhK2ouK9BmbGpXGz2EHKtKqynSyuupwJOo/edit
Hi Michael,
Thanks for this valuable comment. The RP report was the first time for me to learn about the attribution of a certain value to a life saved based on age. Once you are aware about it, you see it and understand it, but it is not really discussed. I found it quite difficult to work with these values as it somehow dilutes/obscures what the findings were. Additionally I find it morally challenging as the people who benefit from the intervention might value these lives completely differently.
Not sure how we can handle that well in our communication without getting people lost in technicalities, so if you would have suggestions for that I would greatly appreciate that.
Kind regards,
Niek
One more addition --> we have planned to use all feedback and insights from this Forum to further sharpen our own evidence overview which we have created on notion. So our own interpretation and representation of the evidence will be improved. If you are interested, please have a look. All feedback (positive and negative) is welcome and will be used to further improve the overviews. https://goal3knowledgehub.notion.site/public-knowledge-hub?pvs=143
Specific recommendations or suggestions for further research (beyond a trial as we already have planned that but will need funding first) are also much welcomed.
Thanks Martijn. This is the kind of critical reflection we hoped for when we opened this up, and I’m grateful you took the time to go through the paper, its supplement and the review history in this much detail. These are important points, and they add nuance to how the evidence should be read.
On the conflict of interest: you are right. Our commercial interest should have been declared from the first submission, and it wasn’t until the final version. That was an oversight because we did not handle the submission process and we assumed it was done, not a deliberate choice, but it remains a mistake and I share responsibility for it as a co-author. Readers should weigh the paper with that in mind. The same applies to the RP report: GOAL 3 commissioned and paid for it.
I do want to respond to one word: “integrity.” I understand why the late COI declaration raises that question, and that one is on us. But I’d ask you to separate it from the rest of the work. The study was designed, run and analysed by researchers from six independent academic institutions in Malawi and the Netherlands, with GOAL 3 staff contributing to data collection and writing, not the analysis. The full results were published, including the HDU result that was not significant and the increase in crude HDU mortality, and the data are available for replication. Questioning the methods is fair and useful, and I will aim to get the answers as soon as possible. Questioning the integrity of the researchers, many of whom have no stake in IMPALA, is a different claim, and I don’t think that does justice to all the people who have contributed. I’d appreciate it if you’d reconsider that framing.
On the statistical points: I’m a clinician, not an epidemiologist, unfortunately the methods in this study (TMLE, the matched sensitivity analysis, how the estimates are defined) are beyond what I can judge with confidence. I don’t want to explain/defend something I can’t fully assess. I’ll ask the lead authors to respond to your points on the HDU estimate, the matched analysis, the case-mix adjustment and the data breakdown at St Luke’s, and I’ll share their answer here. The paper says anonymised data are available for replication, and I’d support an independent reanalysis. I’ll also ask Rethink Priorities to respond to your point on how they weighed this study, since that question is fairly theirs to answer.
Some broader context. I agree the Zomba HDU result can’t carry weight on its own, and that the ward-level results depend on spillover, which this study did not test directly. That’s why it may help to look at the rest of the evidence:
We understand our evidence is not super-strong, eight of nine mortality estimates point in the same direction, but only some are statistically significant. None are randomised, and most were co-authored by GOAL 3 staff. A consistent direction makes chance less likely, but it doesn’t remove biases the studies share, such as before-after confounding. So my honest summary is that the evidence points towards a benefit but does not establish its size, and your critique makes clear the uncertainty is wider than a single discounted figure suggests. That’s also why we still want an independent, prospective controlled evaluation alongside scale-up, as discussed with Nick above.
Thanks again. This is exactly the kind of scrutiny that makes the evidence base better and helps to improve our understanding as well where we have blind spots and need to make additional steps, which was also one of the key reasons to ask RP to assess our evidence.
I hope the process will also help to build your confidence in us and that we are as truthful and transparent as we can be in search of improvement and sharpening our reasoning, evidence (including interpretation) and expanding our impact.
Regards,
Niek
Ministries of health are not passive recipients of aid in our model, their buy-in and willingness to commit resources is fundamental for success and in our perspective the pathway to both scale and sustainability. It is indeed true however, that if I would come with funding they would gladly accept it. Increasingly we see that they are requesting funders to support in purchasing IMPALA One of the key reasons we would like to the Trial is that it will make it easier for them (and funders like UNICEF, UNITAID etc) to justify this in policy and budgeting. So at this stage we see significant buy-in and commitment from governments in the scale-up, but freeing up own resources at sufficient degree to buy entire systems is not yet feasible. We think we can also get there without the trial, but the trial would help a lot. We are also confident that we can easily deliver this trial together with our partners, as we already drafted the protocols and plans to that.
As with regards to your standpoint on RP's assessment --> would you be able to explain why you are so steadfast about it not being correct? Right now you make a claim that they are overstating the effect, but there is a 72% discount already in their estimated effect, which has been largely subjective based on study design. I wonder what arguments you would have to say their assessment is not correct and that the effect should be closer to 0 beyond the weaker study designs.
In my view the fact that the patients before and after where matched for severity in the pediatric design and that we have a controlled interrupted time series for neonatal care is also a quite strong design. (https://researchonline.lshtm.ac.uk/id/eprint/4648480/) And last but not least that all evidence points in the same direction makes chance alone very unlikely.
One thing that is also worth considering You mention the confidence interval is very large which is because the occurrence of the event (death) is quite rare. However if you look at the primary outcome of Critical Illness Events which is an intermediary outcome to mortality and is a lot more frequent, the confidence interval is a lot smaller so the claims about those are quite robust. Moreover the supportive evidence relating to impact on workload, stress levels and confidence of health workers is also important. In general our intervention achieves its effects not just through better monitoring, but also by freeing up time of health workers. This has also been quantified in multiple studies.
As with regards to other studies, I am afraid I must agree that there is hardly any good studies out there within our population. There are several studies on early warning scores, but few on monitoring and especially not in children. Why I believe it works well in this population and why this is different from many other monitoring interventions
a) it is as much about unburdening health workers and freeing up their time as it is about getting better data on what is happening with the child. Our data show health workers consistently report reduced workload and stress levels after implementation. Also direct observation shows it saves a lot of time (from 3.3 hours per shift to 1.8 hours per shift)
b) these are very high risk children, the standard of care is very little if any monitoring, it is easy to improve from there and get better outcomes
c) interventions are relatively simple and readily available (IV fluids, oxygen, antibiotics and glucose, for neonates it can be as simple as rocking the body to prevent severe apnea)
d) as mentioned it is not just monitoring, it is embedded in an entire program of training and continued support with a quality improvement component. Therefore we address a much broader range of potential barriers to timely, quality care then just the lack of vital signs monitoring
In general I feel that there is a huge lack of attention on monitoring in these settings. It is often an afterthought and even in very large programs oxygen and other treatments are prioritized over other things. So for me this is one of the main reasons our effect sizes can be so great. To me monitoring is the foundation of hospitalized patients, especially the most critical/vulnerable patients. The lack of attention on this and lack of awareness about the gaps are huget bottlenecks to improving quality of care.
A) We want it to be representative so only selecting referral hospitals does not do the job as it will not inform a ministry of health what will happen in rural areas. The challenge is that hospitals vary quite a bit, so you have to match them first for certain characteristics and then randomly assign them. The larger the variation the more hospitals you will need, hence we came at 72 through our power calculations. The challenge is most funds only go up to 2 or 3 million USD
B) I think you are right from where we are today, but there have been many moments where it was likely we would not survive. We have our own development team, registrations to maintain all requiring significant investments. If it takes too long, likelihood of dying in the valley of death will increase. There are very few innovators who are actually successful in public health systems for this reason.
Scaling slow also has high opportunity costs. We have made calculations based on our growth projections (hospitals reached) and our impact per hospital (mortality data). I can not share these now, but let's use a fictive scenario that is close to our estimates:
Let's assume Rethink Priorities assessment is right and each hospital using IMPALA will save 7 newborn lives per year and 12,2 pediatric lives per year. If we grow according to our plans we will reach~1000 hospitals by 2030 and IMPALA will help avert ~19,200 deaths every year.
If this is delayed and only 500 hospitals are reached, this means a difference of ~9,600 lives saved in a single year and cumulatively a lot more. At the levels of our own results this would be 4-5 times higher. Of course I also understand it could be significantly lower (but as rethink priorities said even at 1-2% reduction it would still be a good investment). The longer we wait the higher the opportunity costs will be.
My point is not that we should release all breaks and all funding should go to us to scale. However I think it is more than justifiable to invest significantly in a large(r) scale program with thorough evaluation, which could yield results a lot faster and generate more decision critical evidence.
As a few follow-up question to you (and the rest of the forum): What study results (number of sites, quality etc), not from a trial, would convince you and why? If only a trial can convince you why is that? What evidence does it deliver that routine evaluation at scale could not?
C) In any research setting there will be research staff and a lot more data collection, this by itself has a huge effect on how care is provided. Moreover not all sites will be suitable for it, creating a significant selection bias. Therefore the performance in (optimal) trial circumstances often has limited meaning for what it means in real life. Moreover variations across countries, will likely influence success of the intervention. So generalizability is also limited (Why would someone in West Africa, South-East asia or the middle east believe the trial from East Africa) Real world evidence solves a large part of this, whether if it is implementation research or derived from the real world evaluation. We look at each installation for usage, adoption and impact on health workers stress and burnout, where possible (if funding allows) we look at impact on mortality. While the quality of the evidence may be lower, it says a whole lot more about what is actually happening within the specific hospital/country and provides opportunities to intervene (either through us, or the hospital itself) Seeing this over multiple hospitals in one country will help a lot more with decision making then a (potentially outdated) trial from 5000km away (as a figure of speech).
Again, not opposing a trial here just wonder if it is the right instrument for the stage we are at. Just to provide a different perspective. A 5 million implementation program, would allow me to go to 200-300 hospitals in different countries and perform a thorough monitoring and evaluation program in parallel which can look at before-after differences, but also at differences between other hospitals. Those results would be available within 1 year after implementation, so likely 2 years after a grant was awarded.
D) Don't think Claude is accurate. Without a verifiable source on the mortality drop that answer is pretty useless, beyond that it is not wise to assume a conclusion that this is common based on one site. Data quality is notoriously bad in this setting and there is severe under reporting. We have solved this by diving into individual patient files hand by hand (not us, but our research partners)
The study you cite is hardly comparable in my view
- general wards versus ICU/HDU
- High resource settings only - high levels of staffing and no lack of monitoring equipment
- Only adults
- Vast majority is surgical patients
- total number of patients only 1284 over all studies combined
- relative rare occurance of the events making them statistically underpowered to proove significant impact
Moreover if you dive into their discussion you also find that over multiple systematic reviews all findings are consistently positive favoring monitoring, yet not significant. That is relevant to our discussion, because one of the key conclusions is that even at 1-2% mortality reduction IMPALA would still be cost-effective against any bar.
Hi Nick, thanks for your message. Happy to jump on a call myself as well to dive deeper feel free to email ([email protected]) or text via the chat function of the forum (if it has that)
as a first quick reflection/response, hopefully I have more time later this week but here are a few reflections, and apologies for not following your exact numbering.
A) we have been trying over the past 4 years to get trials funded (EDCTP, givewell, EU funding, Gates) without success. There are some ways to make it lower cost (lowest we got was about 2,5M, but that also reduces quality and strength of evidence). In between time we have done what we could through different smaller sources of funding to get the best evidence possible. Agree by the way that blinding is not needed and not relevant and that a large effect actually comes from the behavior change due to its clear presence on the ward. Also randomization is not an issue as long as control sites also get the intervention.
B) trials can be great, but if we wait for those results to come out before scaling we would likely not survive as an organization. This is not unique for us, but for all innovations and a major bottleneck for innovative solutions in general. Moreover, 3 years of waiting to scale and finding out that the results are same, would create a huge amount of deaths not averted, happy to provide more precise estimates at a later stage. Or plea is not to skip the trial, our plea is to do it in parallel.
C) While I like trials I actually think real world evidence is better or at least as important. With monitoring and many other interventions it is not about if they work, but how do they work in a very complex environment that is under-resourced and understaffed. In other words, if I would be the minister of health, I would value evidence from 100% of 50 sites in a real world setting a lot higher than the evidence from the intervention under trial circumstances. Just to be clear --> we are doing all this (we are currently running a controlled interrupted time series in multiple countries and multiple other impact evaluations are still ongoing) and still want to do the trial if we can get the funding for it.
D) A trial as the definitive answer to answer the question if something should be scaled is not rational from a perspective of levels of uncertainty. In my view the lower bound of the margin of certainty just needs to be above (or close to) the treshhold because if it is above that level it would not be rational to say we need a trial first before scaling it up, because the statistics already say it is highly unlikely that it is. I sometimes use the picture at the bottom to describe that (NB if evidence changes the direction of the arrow may also change). Of course it is good to discuss if you agree to the estimated impact and the margins of uncertainty to that which Rethink priorities found, because I do think that is important to agree on (or disagree and find ways to close the gap)
E) too salesy --> I think you may underestimate how important the technology, service-model and business model are compared to anything else that is out there. There are dozens if not hundreds of changes we have done and are continuously doing to improve the intervention (at GOAL 3 level) and at the facility (to improve adoption and usage at facility level) all embedded in the business model which allows us to do continue to do this over time. We do not describe this here in this post to sell or brand our solution, but also to make clear that just putting a monitor down will not have the same effect.
Last but not least: it is also a product of passion and enthusiasm that comes from building 8+ years towards this solution. I just can't be fully objective in how I describe our solution. Firstly because it is the answer to the problems I experienced myself when working in the field, secondly I think there are a lot of lessons to learn from our success that can be used by others. I hope you can accept that (and maybe even appreciate it ;-) )
F) thanks again. Really appreciate the open discussion. Would be great to connect