Comments
TLDR: Autoinjectors don't solve the real bottlenecks to getting more livesaving tranexamic acid and antivenom to patients in LMICs.
Akhil and Georgia wrote a compelling article about autoinjectors in the great new InDevelopment magazine. However, they miss or understate important reasons why autoinjectors won't solve the real bottlenecks that stop lifesaving drugs getting to patients in LMICs. I thought this was an important critique to put out there, as there are many cool candidates for Advance market commitments, perhaps more money soon to fund them, and we should choose wisely.
I like AMCs for new technology. They’ve made a huge impact in the past, and will in future. I love the work Akhil and crew are doing on the neonatal sepsis test AMC - if this test came to fruition, it could change the face of neonatal care. I just don’t see a clear pathway for autoinjectors saving lives in LMICs, and can’t see a strong case for AMCs for their case studies of Tranexamic Acid (TXA) and antivenom at least.
The authors outline the problem well. Far more people need to get TXA and antivenom, far faster. Both interventions deserve more research and work. But I think the authors misdiagnose why health workers don’t give these drugs fast enough.
Why don't we give enough tranexamic acid?
The main reasons women don’t get TXA for Post-Partum Hemorrhage are that the medication often isn’t available at health facilities, and that midwives are still learning to give TXA as part of newish protocols. The problem isn’t that IV administration causes long delays. TXA is still a newish PPH treatment - it was recommended by WHO in 2017, but countries are still concerned about product quality, as there remain no WHO pre-qualified providers. Countries have only recently added TXA to their national guidelines.
1. We can’t yet give TXA into the muscle (IM)
The authors’ statement “TXA does not have to be delivered by IV” is incorrect and could be dangerous.[1] The WHO recommends giving TXA IV. We don’t yet have evidence that IM works in practice. The study the authors cite only shows that IM TXA can produce therapeutic levels in the blood. The study itself states
“Further studies of i.m. TXA in pregnant women are needed to examine the impact of the increased volume of distribution and increased renal elimination that are seen in pregnancy. Other studies needed include comparing the efficacy and safety of i.m. and i.v. TXA in women who are bleeding or at risk of bleeding after childbirth”.
Trials are now testing whether IM might work in practice. If it does, that’s great news, because IM would make TXA far more accessible.
2. We can do intramuscular without autoinjectors
Let’s assume that IM TXA does work well. We can use this to increase medicine access without autoinjectors. We give IM antibiotics, antimalarials and pain relief all the time in LMICs - I think we actually give injections in the rear-end too often here. It’s also a strawman to compare IV and autoinjection - we should instead compare normal IM administration vs IM autoinjection. With normal IM injection, a health worker draws the drug from a vial, which adds only 1–3 minutes.
3. It’s irresponsible to give TXA at homebirths
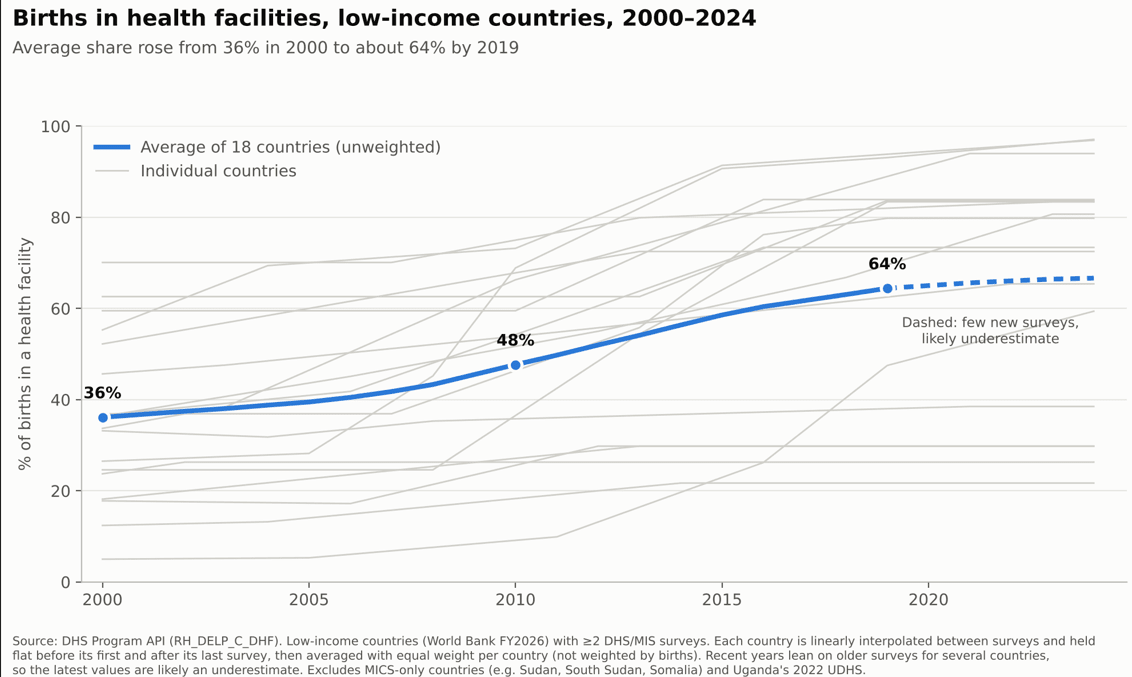
This suggestion by the authors would likely do more harm than good. Homebirths without skilled attendants are too dangerous for us to encourage. Getting women to a health facility where there is a skilled birth attendant is critical to saving women’s and babies’ lives, which is why we do everything we can to prevent homebirths, not support them. Most of the global health community agrees that giving medications to traditional birth attendants (TBAs) legitimises a dangerous situation. Pro-facility delivery policies have helped double facility delivery rates in 20 years, and contributed to plummeting maternal and infant mortality rates. In Uganda, traditional birth attendants are slowly fading into obscurity, which is great for women’s health.
In the 70s and 80s, global health programmes trained TBAs to deliver babies at home and give medicines like oxytocin. This approach largely failed. Birth brings a wide range of complications that TBAs couldn’t manage well. Even the study the authors cited where they gave oxytocin at home didn’t show clear improvements in outcomes.[2]
4. Non-medics won’t give TXA after accidents
Of all their examples, I think TXA application after road accidents might have the most potential. In theory, policemen or other first responders could carry an autoinjector to accidents and get TXA to patients quickly. Unfortunately, it’s unlikely that non-medics will agree to give medication. In most sub-Saharan African countries at least, there is a strong cultural norm that only health workers give injections. Even in high-income countries, non-medical strangers rarely give medication. Sayana Press is a successful injectable family planning device, designed for self-use. Despite heavy investment in training and education, most women still don’t inject themselves. Of the 7 million doses of Sayana Press that PATH tracked, only 1 in 4 was self-given, with the remainder given by health workers.[3] And Sayana Press is a planned, self-given injection, which has fewer cultural and behavioural barriers than an unplanned, stranger-given injection.
In Uganda, if you give someone medication or help after an accident, you become partially responsible for their wellbeing. Good Samaritans do help others all the time, but they know that they will bear some financial and even future-care responsibility for the patient. This cultural norm might sound strange, but it hugely affects care after accidents.
I can’t think of any injection which is given by a non-medical stranger in sub-Saharan Africa. Overcoming this cultural norm might be possible, but would be a mountain to climb over years or decades.
Antivenom
The authors are correct that there is a big problem with access to antivenom. They diagnose the problem well - snakebite victims take too long to reach a health facility, and then patients often don’t get antivenom even when they reach the facility. But the main reason is cost, not that the antivenom is too hard to give physically. They also discuss the promise of giving antivenom IM. This could be helpful but, as already discussed, it doesn’t need an autoinjector.
Cost remains the biggest problem
Antivenom is still so expensive that it is only practical for larger facilities to stock it. Cost has come down a lot in India, but remains $100 to $300 a treatment. Because antivenom is scarce, health workers rarely use it, so they lack the skill and confidence to give it.
Six hours is time enough
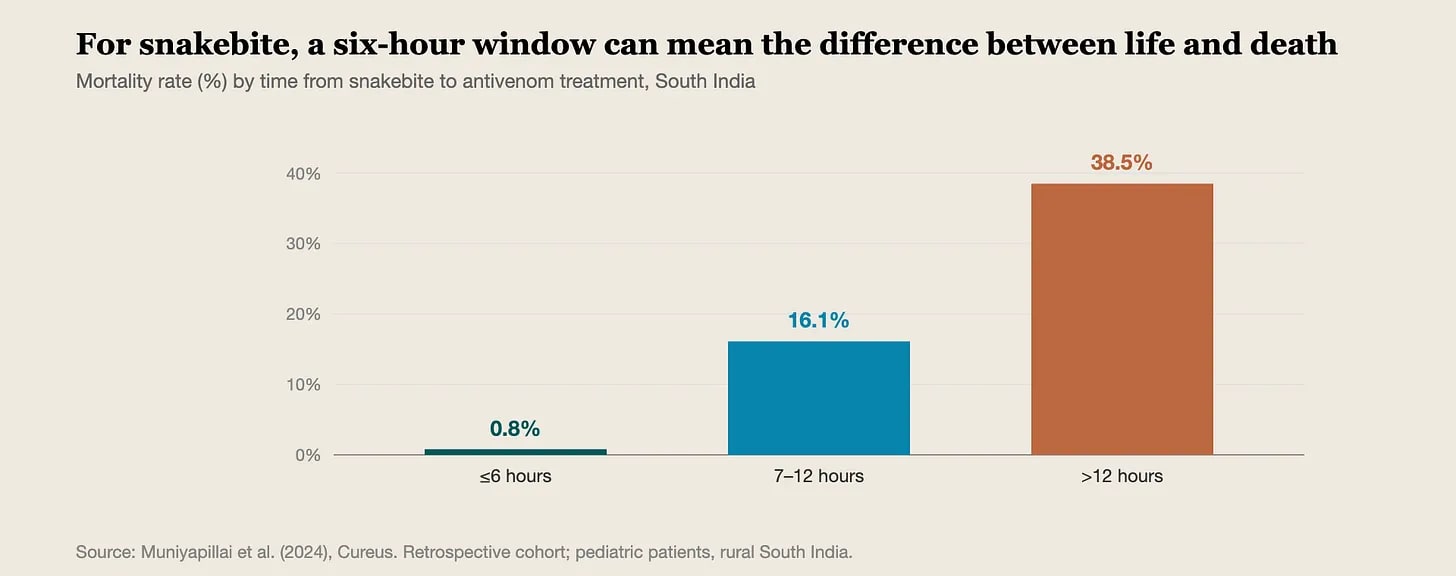
The authors’ graph shows that we only need to give antivenom within 6 hours of someone getting bitten. Perhaps 99% of Indians live within 6 hours of a health facility. The problem is that the antivenom isn’t at health facilities close by - we don’t need to have antivenom in every village.
10+ autoinjectors per patient?
The standard treatment for envenomated snakebite is 10–20 vials of antivenom. It seems implausible that non-medics would give 10–20 vials via different autoinjectors.
What we need is cheaper antivenom in every health centre[4]. I think this would solve the lion’s share of the snakebite problem. If it didn’t, then perhaps we could look for other solutions.
I still think there could be value in autoinjector use in LMICs. But for the two case studies presented, TXA and antivenom, I don’t think autoinjectors can transform the big access problems.
- ^
I think the authors should delete this statement in case some medic takes it seriously.
- ^
I’ll note that this approach is still debated and there isn’t a strict consensus. A significant minority of experts think TBAs should still be integrated into the system, but that’s the contrarian, not mainstream, view.
- ^
Some orgs such as Lafiya Nigeria have succeeded in encouraging home-injection. Most of their doses are self-administered. This is, however, an unusual situation where there is great stigma about visiting health workers to get family planning.
- ^
A potential AMC candidate!


[Nick sent an early draft a few days in advance, which I understand he has since iterated on]
Thank you for engaging- we appreciate and encourage it. There are valid points here. But the critique does not engage the existing evidence base, misreads what we claim, strawmans our arguments, and creates false dichotomies between things that are complements.
Before diving into 6 specific areas, I’ll respond to your high level claim
, “"Autoinjectors won't help LMICs - they don't solve the real problems." ... "They have just misdiagnosed the reasons why these drugs aren't given. Autoinjectors won't solve those problems."
At a high level, our piece does not say autoinjectors are the only answer or even the most cost-effective answer. It says that a ready-to-use intramuscular (IM) format removes one specific and important barrier (the need to site an intravenous (IV) line and run an infusion), and that a pull mechanism such as a prize or an advance market commitment could bring that format to market. We do not claim it is more cost-effective than stocking the drug or training midwives; we do not recommend autoinjectors over prefilled syringes; we do not recommend an AMC over other market-shaping mechanisms.
It is really important to be clear that there is no single "main reason" women do not get TXA. Supply, guidelines, training, detection, route, and who is permitted to give the drug all bind at different points in the system, and the piece addresses one of these constraints. The woman bleeding after a home birth two hours from a facility, whom you set aside after noting that a third of births still happen at home, has a real problem. That a given intervention does not solve the entire or largest problem is not an argument against it.
1. Availability is improving fast — and fastest at the facilities you say it won't reach
“"The main reasons women don't get TXA for PPH are that the medication often isn't available at health facilities, and that midwives are still learning to give TXA as part of standard protocols. TXA is still a newish, relatively unknown PPH treatment ... These are hard, solvable problems."
Availability is improving fast, and fastest at the facilities you say the device will not reach. TXA was not on the WHO Essential Medicines List for PPH until 2019. Since then: 71% of 31 surveyed LMICs have it on their national EML, 77% in national PPH guidelines, and 65% in the public-sector midwifery scope of practice; one advocacy programme took 10 of 14 sub-Saharan African countries through a guideline-revision process and reported 10 of them progressing by by 2022; and WHO made TXA a first-response component of the MOTIVE bundle in October 2025. UNFPA, which buys and ships maternal medicines to the poorest countries, did not include TXA in its 2023 supplies report but did in 2024, where it is now a listed commodity across 54 countries. WHO prequalified a TXA active ingredient in September 2024, which will allow manufacturers to make versions of the drug that UN agencies and national programmes can buy with confidence. At $0.11 an ampoule in Indian public facilities, it is a robustly cheap medicine.
These changes are not just concentrated at the national, guideline level - TXA is being increasingly authorized at lower healthcare levels. South Africa approved TX A or nurses at all levels in July 2023. Kenya moved it from Level 4+ hospitals to all levels where women give birth in 2024. Nigeria's first national PPH guideline (October 2024) recommends TXA availability nad use at all births .
Yet just because we now have TXA in the building, does not mean it is getting to patients inside the window where survival benefit falls about 10% per 15 minutes. You have diagnosed the first gap and declared the second solved- more on this in Response 3.
2. "We can't give TXA into the muscle yet"
Nick: "The authors' statement 'TXA does not have to be delivered by IV' is dangerous and incorrect. The WHO recommends giving the drug IV at all times, we don't have sufficient evidence IM works yet in practice. The study the authors cite only shows that IM TXA can produce therapeutic levels in the blood. The study states that 'Further studies of i.m. TXA in pregnant women are needed ...' Until we get a clear yes on that, we can only give TXA IV."
This is categorically false, and a neglectful misread of what we write. We do not claim IM TXA is approved. Our piece says the evidence is emerging — which it is, and there is more of it than we had room to cite.
First, you quote the line that "Further studies of i.m. TXA in pregnant women are needed", which comes from the 2022 healthy-volunteer crossover trial in the British Journal of Anaesthesia. That study was published in 2022. The study it called for was done the following year: WOMAN-PharmacoTXA randomised 120 women giving birth by caesarean section in Pakistan and Zambia and found IM TXA reached therapeutic concentration within about 10 minutes, stayed there for more than four hours, inhibited fibrinolysis, and caused no serious maternal or neonatal adverse events. You are quoting a 2022 call for a pregnancy study as evidence against us, when the 2023 pregnancy study exists and was positive.
Second, pharmacokinetics, have now been measured in three human populations. Bioavailability was 0.77 in bleeding trauma patients, with absorption unaffected by shock ( an obvious objection, tested and answered in that study); 1.0 in a volunteer crossover RCT and 105% in a seven-study individual-participant meta-analysis. In postpartum women, as mentioned, WOMAN-PharmacoTXA randomised 120 women in Pakistan and Zambia and found IM "inhibits fibrinolysis within 10 minutes and may be a suitable alternative to IV," with no serious maternal or neonatal adverse events.
We also have efficacy in animal model, not just blood levels.. Swine haemorrhage: 97% bioavailability with complete reversal of hyperfibrinolysis; a 2024 study found lysis of 87% in controls versus 1.96% IM and 1.5% IV — "bioequivalent and equally efficacious"; further porcine work agrees; a 2026 autoinjector study found blood loss comparable to IV. UK JRCALC has authorised the IM route since 2021 where IV access is not promptly achievable . That is a national clinical guideline, not a preprint.
"We can only give TXA IV" is false as stated. UK JRCALC has authorised the IM route since 2021 where IV access is not promptly achievable . That is — a national clinical guideline, not a preprint. CRASH-4 is giving IM TXA prehospital, by paramedics, today. I'M WOMAN has recruited 31,420 of a planned 40,000 women; we have discussed the preliminary results with the investigators and are not at liberty to share them. BARDA has committed up to $186 million to Rafa Laboratories and funded MACH32; the UK MoD put £5m into a TXA autoinjector; the US Army has recommended developing one.
The WHO is actively exploring alternative routes of TXA administration; the WHO PPH Roadmap ranks alternative routes of TXA administration as the number one innovation research question in the field, while the 2025 consolidated guideline calls evaluating them "a research priority."
"We can only give TXA IV" describes today's guideline, not the state of the science. Our claim is conditional: if the trials are positive, a product and a market should already exist rather than the usual decade of lag. If I'M WOMAN is negative, we will revise our recommendation.
3. "We don't need an autoinjector to give intramuscular meds"
Nick: "We give IM antibiotics, antimalarials and pain relief all the time in LMICs ... It's a strawman to compare IV and autoinjection - we should instead compare normal IM administration vs autoinjection. IM medication does need to be drawn out of a vial, but this doesn't take long. I can't see autoinjection saving more than a 1-3 minutes in almost all settings a health worker would give the medication."
First, this is a strawman. We are not wedded to autoinjectors - our piece says the drug could be given “as two 5 mL prefilled syringes, which needs no reformulation at all, or — with further engineering to concentrate the formulation — as a single autoinjector”. The argument is ready-to-use intramuscular format versus drawing up and running a ten-minute intravenous infusion.
Second, you have understood the benefit room thing. The largest effects are as follows:
1.Whether it is given at all. In RAMPART, 893 patients were randomised to an IM autoinjector or IV, given by trained US paramedics with full supplies. It found that 7% of the IV arm never received the drug because access could not be obtained, and seizures had stopped on arrival in 73.4% versus 63.4%. A UK physician-paramedic service that merely pre-drew TXA gave it more often and 20 minutes sooner. And cannulation is difficult: veins flatten out as someone bleeds, the patient may be thrashing about (particularly after trauma), and siting a line competes with rubbing up a uterus and calling for help. The Zambian investigator on WOMAN-PharmacoTXA put it directly: "There is no point in having TXA when cannulation is not an option."
2.Whether it is given correctly. Across 37 in-situ anaphylaxis simulations in 28 institutions, at least one medication error occurred in 68% of cases. With oxytocin in Uniject, Indonesian midwives "overwhelmingly preferred it to standard needles and syringes", with dose accuracy, sterile technique, and disposal all improving; 98% of Vietnamese midwives found Uniject easier than ampoules.
3.Who may give it : this effect is quite significant. WHO treats the delivery format as part of what makes a task safe to perform by lower-level cadre healthcare workers.. In OptimizeMNH, auxiliary nurses are recommended to give oxytocin for PPH using a compact, prefilled auto-disable device, while lay health workers giving the same drug with a standard syringe is research-only. Same drug, same route, same indication - but the device decides the cadre. A device format a health-post worker or basic-level ambulance crew can be authorised to use does not shave three minutes off an injection — it converts a patient who would have received nothing into one who is treated.
4. "It's irresponsible to give TXA at homebirths"
Nick: "This would probably do more harm than good ... The majority of the Global Health community agrees that giving medications to traditional birth attendants legitimises a dangerous situation ... Pro-facility delivery policies have helped double facility delivery rates in 20 years, and contributed to plummeting maternal and infant mortality rates ... In the 70s and 80s there was a push to support TBAs to deliver babies at home and give meds like oxytocin. But this failed - outcomes didn't improve when TBAs were given training, support and meds like oxytocin ... Even the study the authors cited where they gave oxytocin at home didn't show improvements in outcomes."
We agree that more women should give birth in facilities. Our piece does not propose supplying TBAs, nothing in our argument depends on unattended home birth, and most of the benefit we model is in facilities. We are trying to innovate for the world today, in which some women give birth in referral hospitals, some in lower-level facilities, and some at home.
Health centres account for 40% of Ethiopian births, against 16% in hospitals; 75% of Tanzanian dispensaries offer delivery care, but only 60% of delivery facilities have a provider on site or on call around the clock. 60% of sub-Saharan births have a skilled attendant, and 19 million African births are projected to have none in 2030. Skilled attendance exceeds facility birth in eastern Indonesia, 86% to 72%.
A skilled attendant is also not the same as a prepared one. "Are skilled birth attendants really skilled?" found 166 attendants scored 48% on skills items and 46% on active management of the third stage; only 36% of providers observed at 2,317 births across six sub-Saharan countries had been trained in the previous three years; across 24 Nigerian primary health centres, only 55% of nurse-midwives were very confident managing PPH. A drug format that is harder to get wrong matters more, not less, in these scenarios.
On the oxytocin trial you are factually wrong. The Ghana cluster-randomised trial had community health officers give oxytocin in Uniject at home births: PPH fell from 5.5% to 2.6%, RR 0.49, p=0.02, with no maternal deaths, uterine ruptures or needlestick injuries. Cochrane concluded it "probably decreases the incidence of PPH." It cannot be cited for the claim that it did not work. And the line you call settled is already drawn elsewhere: WHO fully recommends lay health workers administer misoprostol to prevent PPH, and community distribution across seven countries raised coverage substantially, that review finding "fears of misuse... are not supported by evidence."
5. "Non-medics won't give injections" — no evidence is cited, and your own example refutes it
Nick: "There is a strong cultural norm in most Sub-saharan African countries at least that only health-workers give injections. Sayana Press is a successful injectable family planning device, designed for self-use. Despite huge funding devoted to training and education, most women don't self-administer the medicine as intended. Of 7 million doses ... only 1 in 4 doses were self given ... In Uganda, if you give someone medication or help after an accident you become partially responsible for their wellbeing ... I can't think of any injection which is given by a non-medical stranger in sub-saharan Africa."
First, the people we have in mind are not non-medical strangers; they are health-post workers, auxiliary nurses, and basic-level ambulance crews: people who already work in health care but are not licensed to site an IV line or would find an IM device easier and quicker to administer (which we know they already do). Moreover, they aren’t also necessarily located in sub-Saharan Africa, which you focus on despite us not specifying this geography (as of 2013, the greatest burden of road-traffic incidents is in China, India, and Indonesia).
On Sayana Press, your own examples support us. Self-injection rose from about 8% of DMPA-SC visits in early 2021 to 31% by mid-2025 - this is just how adoption generally works (over time, not 0 to 100%). Where women self-inject, it works better. In a randomised trial of 731 women in Malawi, 73% of women who self-injected were still using the method after a year, against 45% of women injected by a provider. Besides; TXA would likely not be self-injected anyway, since it could never be authorized to be administered by a non-medical worker, so this example is somewhat mute. Focusing on the other three-quarters of doses matter more: those injections are given by nurses and community health workers, 47,728 of whom PATH has trained; in Uganda's pilot, around 2,000 CHWs administered all 130,000 doses. A prefilled device moved an injection out of the clinic and into the community. That is the mechanism we describe.
On "I can't think of any injection given by a non-medical stranger”: Beyond contraception: Gadchiroli village health workers treated neonatal sepsis with injectable antibiotics, case fatality falling from 16.6% to 2.8%; Ethiopian health extension workers gave injectable antibiotics at health posts when 90% of families refused referral; Bangladeshi community-level injectable regimens matched hospital care. In emergencies: US lay naloxone programmes recorded 26,463 reversals by laypeople; across Kazakhstan, Kyrgyzstan, Tajikistan and Ukraine lay responders used naloxone in roughly 90% of witnessed overdoses; 74.7% of 919 US school anaphylaxis events were treated with an autoinjector. In Uganda, 154 motorcycle-taxi first responders treated 250 victims in six months, and a 2024 follow-up across Uganda, Chad and Sierra Leone covered 1,291 responders and 2,171 encounters at $51.65 per DALY; in Kampala, 97% of trained police, taxi drivers and community leaders had used a skill within six months. EMS is unavailable to 91.3% of Africans.
And your road-trauma example refutes your own case. In the Western Cape, only 2.8% of 4,094 haemorrhage-risk patients received prehospital TXA despite 82% arriving within the window — because only 4% of providers were licensed to give it, while basic and intermediate providers who cannot give TXA managed 67% of those patients and performed other circulatory interventions in 70–79% of cases. The authors recommend extending scope of practice. The constraint is not culture or willingness; the delivery format dictates who may legally give it.
Liability is your serious point, and it is addressable. India's 2019 Motor Vehicles Amendment Act provides that "a Good Samaritan shall not be liable for any civil or criminal action," and willingness to help rose from 26% in 2013 to 88% in 2018. That belongs in programme design — a fair correction.
6. Antivenom: an AND, not an OR
Cost and cold chain are the first-order constraints, and we said so in the piece. But "time isn't really of the essence" isnt true.
Only 59.4% of children in the Tamil Nadu study behind our chart received antivenom within six hours; a 2026 systematic review of 44 studies found traditional healers consulted first in 40–73% of cases, median delays "often exceeding 6–18 hours," and each hour of delay raising severe-outcome odds about 1.4-fold; across 11 Indian states, 86.4% sought hospital care but only 60.2% received antivenom, with nearly half of reported deaths outside hospital.
Your stocking point compounds the delay rather than replacing it: antivenom was available in 44.7% of Kenyan public facilities; 6.9% of 532 Ugandan cases received it; only 26% of Malawian nurses had ever given it; no Indian district had an adequate continuum of care. A patient two hours from a clinic who sees a healer, reaches a facility with no stock and is referred onward is not a six-hour patient. Transport alone moves mortality — a Nepali motorcycle-volunteer scheme cut case fatality from 10.5% to 0.5%, Karnataka mortality was 7.3% among those consulting traditional healers versus 0.9% — and delay drives the morbidity your cost argument cares about, with median delay of 9 hours versus 5 predicting acute kidney injury.
Your two constraints are also being solved: broadly-neutralising antibody cocktails protected against a 19-species elapid panel; nanobody antivenom outperformed plasma antivenom across 17 African elapids; de novo binders show "remarkable thermal stability" and are "readily manufacturable" and "cost-effective"; freeze-dried antivenom held potency six months at 38°C. When antivenom is cheap and needs no fridge, time becomes the binding constraint — varespladib's signal of benefit was in patients treated within five hours, and WHO's strategy calls for accelerating "first mile" care. You may be right that the device is third in the queue. That is an ordering argument, not a dead end.
[unfortunately due to time constraints, I do not think I will have capacity to engage further]
Thanks @Akhil
I'll engage with more point by point later - but I would completely agree with you if this was really the high level point of your article. I encourage people to read the original article first, and see if I really do "misread what they claim".
"At a high level, our piece does not say autoinjectors are the only answer or even the most cost-effective answer. It says that a ready-to-use intramuscular (IM) format removes one specific and important barrier (the need to site an intravenous (IV) line and run an infusion), and that a pull mechanism such as a prize or an advance market commitment could bring that format to market. We do not claim it is more cost-effective than stocking the drug or training midwives; we do not recommend autoinjectors over prefilled syringes; we do not recommend an AMC over other market-shaping mechanisms"
But I don't think anyone would read your article and then when asked would give the article a high level summary like that. I think its far, far more bullish about the potential impact and cost-effectiveness specifically of autoinjectors than that summary would make out.